


Hip Pain, Bursitis, and Hip Flexor Pain: What’s Actually Going On
Lateral hip pain and hip flexor pain get lumped together often, but they’re usually different problems with different drivers. Here’s what we actually see in the clinic, and what tends to work.
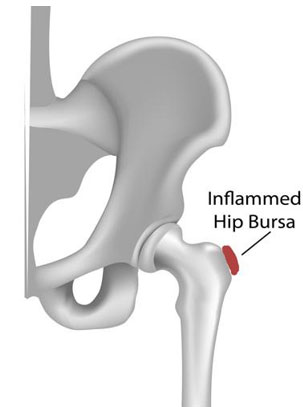
Greater Trochanteric Pain Syndrome (Outer Hip Pain / “Bursitis”)
The broad diagnosis of greater trochanteric pain syndrome (GTPS) describes a collection of problems affecting the outer portion of the hip — historically all lumped under “bursitis,” though the modern understanding is broader. GTPS can involve inflammation of one or more bursae, tendinopathy of the gluteus medius or minimus tendons where they attach to the hip, or both. Weak hip abductors are commonly involved in this presentation — the gluteus medius is one of the muscles most frequently implicated, and weak or inhibited hip abductors is one of the most common underlying drivers we find on evaluation.
GTPS is most common in middle-aged to older adults and affects women 2 to 4 times more often than men. It can affect both hips at once. Roughly a third of patients with GTPS also have low back pain, and patients with hip or knee arthritis appear more likely to develop ongoing complaints.
Typical symptoms:
- Persistent pain on the outside of the hip, buttock, or upper thigh
- Pain aggravated by sitting with legs crossed, standing up from a seated position, prolonged standing, climbing stairs, or high-impact activity like running
- Difficulty sleeping on the affected side
For adults, X-rays aren’t always necessary to confirm the diagnosis, though children and adolescents typically need imaging to rule out other causes. Tell us right away if you notice fever, leg numbness, pain radiating well beyond the knee, or pain specifically in the front of the groin crease — these warrant a different evaluation path.
What the research shows: A 2024 systematic review and meta-analysis in Physiotherapy (Kjeldsen et al.) pooled data from 6 randomized controlled trials and 733 patients with GTPS. Exercise-based treatment produced meaningful reductions in pain and improvements in function — and was specifically shown to be superior to corticosteroid injection for producing a meaningful overall improvement. A more recent 2025 network meta-analysis in the Journal of Orthopaedic Surgery and Research (Wang et al.) reached a similar conclusion when comparing multiple conservative treatment approaches head-to-head. Conservative treatment — the kind we provide here — is successful in the large majority of GTPS cases.
Snapping Hip / Hip Flexor Tendinopathy
A different but related presentation involves the psoas — the deep hip flexor muscle that runs from the lower spine, through the pelvis, to attach at the top of the femur. Along that path, the psoas tendon crosses several bony prominences at the front of the hip socket. When the muscle is tight, the tendon can catch and release over these bony points, sometimes producing an audible snap — hence “snapping hip,” also called internal snapping hip syndrome or psoas tendinopathy.
This is usually an overuse injury from repetitive hip flexion rather than a single acute injury, which is why it’s also nicknamed “dancer’s hip” or “jumper’s hip.” It shows up frequently in runners (especially uphill running), rowers, track and field athletes, hurdlers, soccer players, and gymnasts.
Typical symptoms:
- An audible or felt snapping sensation with hip flexion and extension (though many cases are silent)
- Deep groin pain that can radiate to the front of the hip or thigh
- Weakness or a limp in longer-standing cases
- Low back pain, often driven by the same weak, tight psoas that’s causing the snapping
This condition gets missed frequently because the snapping itself can be painless and easy to dismiss. We evaluate for it specifically and treat it with a combination of massage therapy, manual and physical therapy exercises, and chiropractic care aimed at both the tendon itself and the mechanical drivers — usually hip and pelvic stability — that are keeping it irritated.
For patients whose GTPS or psoas tendinopathy hasn’t responded to standard conservative care, shockwave therapy for greater trochanteric bursitis is another option we offer, with its own dedicated research base.
FAQ
Do I need surgery for snapping hip or GTPS? Almost never as a first step. Conservative treatment — the kind provided here — resolves the large majority of GTPS cases, and psoas tendinopathy typically responds well to targeted manual therapy and exercise. Surgical release of the psoas tendon is reserved for cases that don’t respond after a genuine trial of conservative care.
I’ve had a cortisone shot for my hip and it wore off. Now what? This is common, and it doesn’t mean you’re out of options. The research actually favors exercise-based treatment over repeated corticosteroid injections for GTPS specifically — a 2024 meta-analysis found exercise produced better overall improvement than injection. We build a plan around the mechanical drivers — often weak hip abductors — rather than just chasing the inflammation each time it flares.
Why does my hip pain seem connected to my low back pain? Because they usually share a driver. Weak or inhibited hip abductors and a tight, overworked psoas both destabilize the pelvis, which the lower back then has to compensate for. About a third of GTPS patients also have low back pain — treating the hip in isolation from the rest of the kinetic chain tends to produce incomplete or short-lived results.
Is snapping hip dangerous? Generally not, especially if it’s painless. The snap itself is mechanical, not a sign of joint damage. It’s worth having evaluated if it’s painful, worsening, or accompanied by weakness, since those signs suggest the tendon has become genuinely irritated rather than just catching.
How long does treatment take? Most patients see meaningful improvement in 4 to 6 visits, consistent with our practice-wide average of 6.3 visits to resolution across all musculoskeletal conditions. Chronic cases, or those involving significant hip abductor weakness that needs to be rebuilt, may take longer.
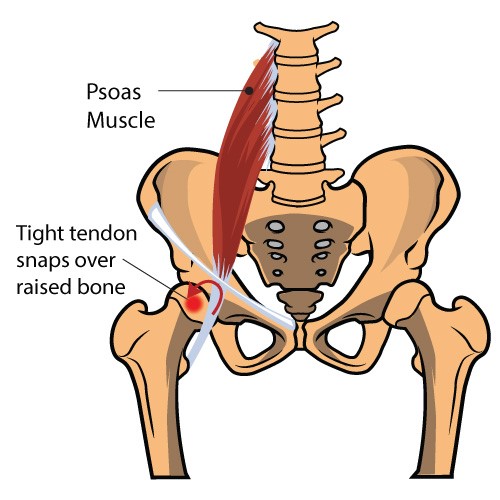
Image on this page provided by ChiroUp.
Coordinated Care, Under One Roof
Chiropractic, physical therapy, acupuncture, and massage therapy are coordinated under one roof with the rest of your treatment plan rather than operating in isolation. Schedule your appointment to get started.